Inside the Danger Zone: Anatomical Maps and Real-Life Cases of Triangle of Death Infections

A routine squeeze in front of the bathroom mirror can derail into a medical emergency within forty-eight hours. Across clinical registries and viral forums alike, patients have shared jarring accounts of minor facial blemishes morphing into systemic crises. In late 2025, reports highlighted the case of an American patient who squeezed a simple comedone near their upper lip and landed in urgent care requiring four concurrent prescription drugs, including high-dose intravenous antimicrobials. As explored in a detailed National Geographic Report, this anatomical corridor, long dubbed the "triangle of death", carries a rare but biologically direct pathway to the human brain.
The fascination with this facial zone stems from an intersection of high-stakes anatomy and mundane human habit. Millions pick at their skin daily without consequence, yet otolaryngologists and infectious disease specialists treat patients every year whose routine pimple popping triggered rapid periorbital swelling, cranial nerve palsy, or life-threatening bloodstream infections. Understanding why this small patch of skin carries such severe biological leverage requires stripping away online hysteria to look closely at cranial vascular architecture.
📌 Key Takeaways:
- The Boundary: The danger triangle forms an isosceles shape spanning from the bridge of the nose down to both labial commissures (corners of the mouth).
- The Vascular Trap: Unlike veins in the limbs, the facial and ophthalmic veins within this zone lack one-way valves, enabling retrograde blood flow directly into the cavernous sinus.
- The Clinical Reality: While catastrophic events like septic cavernous sinus thrombosis remain rare, unchecked bacterial infiltration can rapidly evolve into facial cellulitis, orbital abscesses, and systemic sepsis.
The Facial Map from Nasal Bridge to Lip Corners
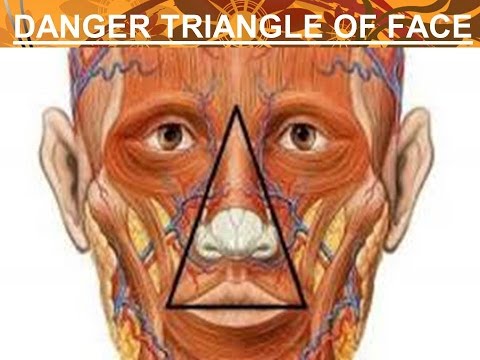
The geographic boundaries of the danger triangle are precise. Draw an imaginary line connecting the oral commissures across the upper lip to establish the base. Then, draw two ascending lines converging at the nasion, the dip at the bridge of the nose directly between the eyes.
This perimeter encloses the entire nasal dorsum, the columella, the external nares, and the philtrum. The soft tissues in this zone sit directly over delicate cartilage and bone with minimal subcutaneous fat. Because the skin here is densely packed with sebaceous glands and hair follicles, it produces frequent micro-comedones, pustules, and ingrown nasal hairs. When individuals squeeze, prick, or aggressively tweeze within this border, they breach the stratum corneum in an area with the densest retrograde vascular drainage network anywhere on the human skull.
The Direct Line to the Brain: Valveless Facial Veins and Cavernous Sinus Blood Flow
The human venous system generally relies on one-way bicuspid valves. These flaps ensure deoxygenated blood travels against gravity back toward the heart without sloshing backward. The head and neck operate on a different set of hydraulic rules.
The facial vein, angular vein, and superior and inferior ophthalmic veins are largely valveless. Blood flows in whatever direction local tissue pressure dictates. When you pinch a lesion, you exert blunt mechanical force down into the dermis rather than merely upward. This compressive pressure can rupture the underlying follicular wall, pushing bacteria down into surrounding capillary beds.
From the angular vein at the inner canthus of the eye, retrograde flow passes effortlessly into the superior ophthalmic vein. That vessel drains directly backward into the cavernous sinus, a pair of blood-filled cavities located at the base of the skull, bordering the sphenoid bone and the sella turcica.
The cavernous sinus is critical neurovascular real estate. Passing directly through each sinus cavity are the internal carotid artery and cranial nerve VI (the abducens nerve). Embedded within its lateral dura mater walls run cranial nerves III (oculomotor), IV (trochlear), and the ophthalmic (V1) and maxillary (V2) branches of the trigeminal nerve. When infected blood pools in this enclosed trabecular structure, the consequences are disastrous.
From Surface Pimple to Sepsis: The Microbial Mechanics
The culprit behind these severe facial infections is rarely exotic. It is usually Staphylococcus aureus, alongside common cohorts like Streptococcus pyogenes or methicillin-resistant Staphylococcus aureus (MRSA). These bacteria colonize the anterior nares of approximately 30% of the global population harmlessly.
The danger begins with mechanical disruption. Pimple popping ruptures micro-vessels, opening an entry portal. Bacteria enter the dermal lymphatics and venous plexuses. Local neutrophils rush to contain the pathogen, generating erythema, heat, and initial induration.
If bacterial replication outpaces the initial immune defense, the infection transitions from localized folliculitis to spreading facial cellulitis. Without immediate clinical intervention, the bacteria trigger micro-thrombi. When these infected clots break free or propagate backward through the valveless ophthalmic channels, septic thrombophlebitis takes hold within the cavernous sinus.
Once colonized, the sinus becomes a breeding ground for systemic dissemination. Patients face high fever, rapid drops in blood pressure, and severe sepsis risk, alongside the looming danger of the infection leaking into the surrounding subarachnoid space to cause bacterial meningitis or brain abscesses.
Progression Profiles: Triage, Symptoms, and Clinical Stages
Differentiating an irritated surface pimple from a burgeoning intracranial infection requires close observation of structural red flags. Clinicians assess these cases based on a progressive cascade of symptoms.
| Clinical Phase | Physical Symptoms & Markers | Pathological Development | Required Intervention |
|---|---|---|---|
| Stage 1: Superficial Folliculitis | Localized erythema | Infection confined to the hair follicle and upper dermis. | Topical antiseptics, warm compress; zero mechanical popping. |
| Stage 2: Spreading Cellulitis | Rapidly expanding redness >2 cm, skin warmth, firm swelling, low-grade fever. | Invasion into deep subcutaneous layers; bacterial replication in tissue planes. | Urgent care evaluation; high-dose oral or IV targeted antibiotics. |
| Stage 3: Orbital / Pre-Septal Involvement | Periorbital edema, chemosis (conjunctival swelling), mild proptosis, throbbing headache. | Retrograde migration through superior/inferior ophthalmic veins toward orbital apex. | Hospital admission, emergency contrast CT/MRI, multi-agent IV therapy. |
| Stage 4: Cavernous Sinus Thrombosis | Bilateral eye swelling, ophthalmoplegia (inability to move eye), ptosis, high spiking fevers, altered sensorium. | Septic clot within the dural venous sinus; compression of CN III, IV, VI, V1. | ICU admission, therapeutic anticoagulation, broad-spectrum IV antimicrobials, potential surgical decompression. |
Medical Imaging and Emergency Hospital Protocols
When a patient presents to an emergency department with escalating facial swelling and neurologic warning signs, clinicians cannot rely on surface inspections.
Diagnostic confirmation requires cross-sectional neuroimaging. A contrast-enhanced Magnetic Resonance Imaging (MRI) with Magnetic Resonance Venography (MRV) serves as the gold standard. High-resolution MRV tracks venous flow voids, directly highlighting filling defects inside the cavernous sinus or ophthalmic veins. Alternatively, a contrast-enhanced Computed Tomography (CT) venogram of the head and orbits can rapidly identify lateral bulging of the cavernous sinus wall, orbital proptosis, and bone erosion.
Treatment protocols move quickly:
- Broad-Spectrum Intravenous Antimicrobials: Physicians immediately start empirical therapy before culture results return. Regimens typically combine vancomycin (to cover MRSA) with a third- or fourth-generation cephalosporin (such as ceftriaxone or cefepime) or metronidazole to neutralize both Gram-negative pathogens and anaerobes.
- The use of low-molecular-weight heparin (LMWH) remains a standard intervention. Clinicians administer it carefully to prevent clot propagation across the circular sinus to the contralateral cavernous sinus, while monitoring for intracranial hemorrhage.
- If cranial nerve dysfunction is present, controlled doses of dexamethasone may be added after starting antibiotics to reduce perilaryngeal and orbital inflammation.
Before the widespread availability of antibiotics in the mid-twentieth century, septic cavernous sinus thrombosis had a mortality rate approaching 80% to 100%. Modern emergency care has reduced mortality to 10% to 20%, but neurological morbidity remains high. Roughly one in three survivors experiences permanent deficits, including partial blindness, strabismus, or localized sensory numbness across the forehead and cheek.
Dermatological Harm Reduction: How to Handle Central Facial Breakouts
Banning the impulse to pick at skin completely runs counter to human behavior. Dermatologists focus instead on targeted harm reduction for the perilabial and nasal region.
Leave blind, deep cysts entirely untouched. Squeezing a nodule that lacks a defined whitehead guarantees inward rupture. Instead, apply a warm, damp compress for ten minutes twice a day to encourage spontaneous peripheral drainage without manual pressure.
Use topical spot treatments formulated with 2.5% to 5% benzoyl peroxide or 2% salicylic acid to kill bacterial colonies and clear the follicular neck chemically. Hydrocolloid pimple patches provide an effective physical barrier. By absorbing excess exudate while preventing fingers from touching the lesion, they eliminate the mechanical friction that pushes surface bacteria into deeper vascular pathways.
If you nick an ingrown nasal hair or experience a localized breakout that begins spreading outward with marked heat, throbbing pain, or facial asymmetry, skip routine cosmetic fixes. Seek evaluation at an urgent care clinic immediately. Early oral or intravenous antibiotic therapy stops the cascade before bacteria reach deeper cranial anatomy.
Frequently Asked Questions (FAQ)
Q1: How common is cavernous sinus thrombosis from popping a pimple?
A1: It is extremely rare. Fewer than a few hundred cases of septic cavernous sinus thrombosis occur annually across North America and Europe combined, with only a fraction originating from facial acne. However, mild to moderate facial cellulitis stemming from skin manipulation in this zone is common and requires prescription antibiotic therapy to prevent deeper progression.
Q2: Why do facial veins lack valves when leg veins have them?
A2: Limb veins require robust one-way valves because blood must travel upward against continuous gravitational pull. In the head and neck, gravity naturally assists venous return toward the jugular veins while standing. The evolutionary trade-off is that any sudden focal pressure can reverse local venous flow.
Q3: What are the earliest warning signs that a facial infection has turned dangerous?
A3: Watch for redness spreading rapidly outward beyond the initial spot, facial puffiness, throbbing pain out of proportion to a normal blemish, and systemic symptoms like fever or chills. If you notice eye tenderness, double vision, or swelling of the eyelid, treat it as an immediate medical emergency.
Navigating Facial Health Beyond Online Alarmism
The danger triangle is neither an internet urban legend nor an imminent death sentence for every stray pop. It is an anatomical reality defined by specialized cranial blood flow. When skin trauma coincides with virulent bacteria like Staphylococcus aureus, this vascular corridor offers an unobstructed path to the skull base.
Treat the zone spanning your nasal bridge to your mouth with caution. Rely on topical treatments, maintain strict hygiene, and leave deep extractions to licensed dermatologists. If an inflamed blemish expands into warm, throbbing facial swelling, set home remedies aside and seek prompt medical attention. Rapid intervention keeps a common skin infection from becoming a life-altering event.
